
Eating Well on GLP-1s: The Nutritional Risks Nobody Should Ignore
Sep 27, 2026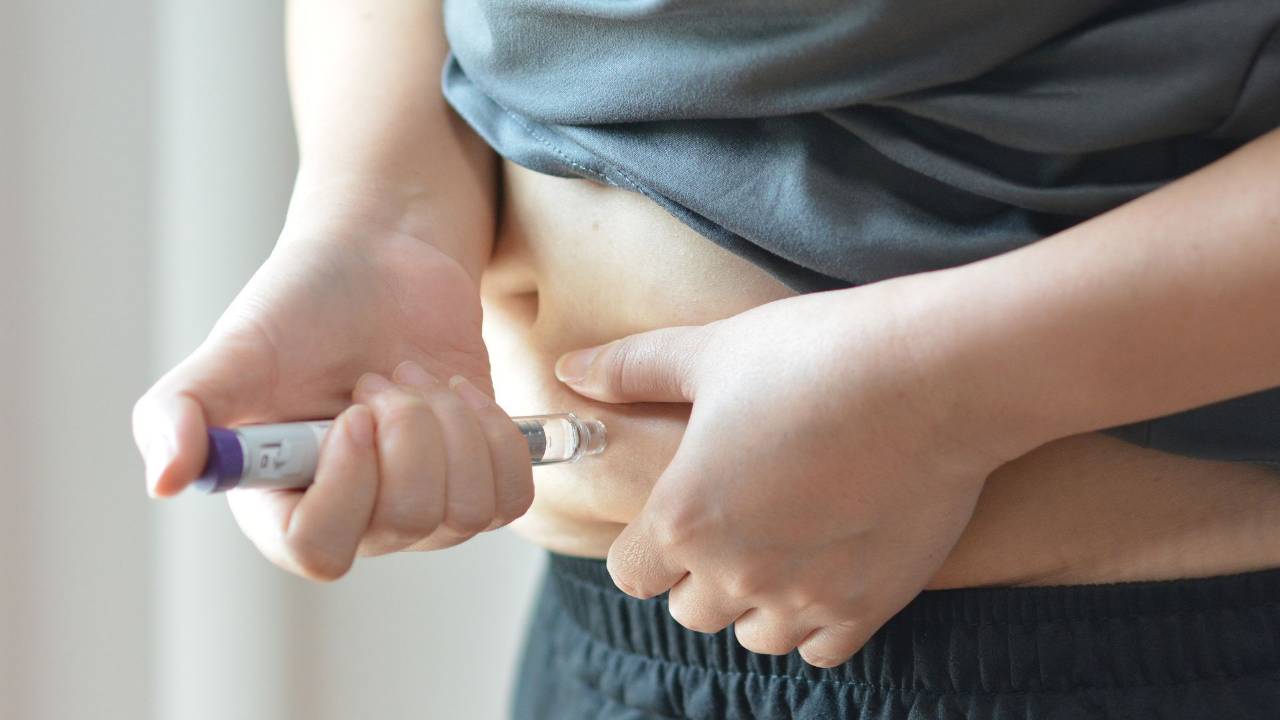
Drugs such as semaglutide and tirzepatide have transformed the treatment of obesity. By profoundly reducing appetite and food intake, they can produce levels of weight loss that were previously difficult to achieve without surgery. But eating substantially less creates a nutritional challenge that deserves far more attention: when every mouthful becomes smaller, the nutritional quality of every mouthful becomes more important.
The arrival of GLP-1-based weight-loss medications has changed the landscape of obesity treatment remarkably quickly. Semaglutide and tirzepatide can produce substantial reductions in body weight, improve glycaemic control and reduce several markers of cardiometabolic risk. For people who have spent years repeatedly losing and regaining weight while experiencing persistent hunger, the reduction in appetite can be transformative.
That reduction in appetite is also precisely why nutrition needs to become part of the conversation.
When somebody taking one of these medications tells me that they can now eat only a fraction of the food they previously consumed, my first thought is not that this is necessarily a problem. Reduced energy intake is, after all, an important part of how these treatments produce weight loss. The question is what remains in the diet once the amount of food being eaten has fallen so dramatically.
A person can consume fewer calories while still obtaining adequate protein, essential fatty acids, vitamins, minerals and fibre. Equally, somebody can eat so little, or eat such a restricted range of foods, that meeting those nutritional requirements becomes increasingly difficult. The medication itself does not somehow provide the nutrients displaced by the reduction in food.
This distinction is becoming increasingly important as GLP-1 and related medications move from relatively specialist treatments into widespread use.
A review published in September 2026 concluded that GLP-1 receptor agonists substantially reduce meal size and highlighted nutritional issues including lean-tissue loss, reduced intake and reported vitamin deficiencies. A separate systematic review found reductions in energy intake of around 24–39% across the studies it examined, while noting that protein and micronutrient intake were rarely systematically assessed. PubMed
The question therefore should not simply be how much weight somebody loses while taking a GLP-1 medication. It should also be whether they are remaining well nourished while losing it.
Appetite suppression changes the nutritional equation
For decades, one of the greatest challenges in weight management has been controlling energy intake in the presence of hunger. GLP-1 receptor agonists alter that equation because they influence appetite and satiety, while also slowing gastric emptying to varying degrees. Tirzepatide additionally acts on the GIP receptor.
The resulting reduction in appetite can be profound. A 2026 systematic review and meta-analysis found that GLP-1-based therapies reduced energy consumed during standardised ad-libitum meal tests by approximately 271 kilocalories compared with control conditions, although the authors noted that habitual real-world dietary intake remains surprisingly poorly characterised. PubMed
This can create an unusual nutritional situation. Someone who previously struggled to stop eating may suddenly need to make a conscious effort to eat enough of the foods they actually require.
That is a fundamentally different nutritional problem.
Imagine somebody whose appetite has fallen sufficiently that breakfast disappears, lunch becomes half a sandwich and dinner is whatever portion can be tolerated before fullness arrives. Their energy intake may have fallen dramatically, but whether that diet supplies enough protein, iron, calcium, zinc, vitamin B12, essential fatty acids, fibre and other nutrients is a completely separate question.
This is why I think the nutritional conversation around these medications needs to mature. The objective should not be to squeeze food intake as low as possible in pursuit of the fastest possible movement on the scales. It should be to create an appropriate energy deficit while preserving nutritional adequacy, physical function and as much metabolically valuable tissue as possible.
Weight loss and fat loss are not identical
One of the most important issues is body composition.
When body weight falls, the tissue being lost is not exclusively adipose tissue. Some loss of lean body mass normally accompanies weight reduction, regardless of whether that weight loss is produced through dietary intervention, medication or surgery.
This matters because lean body mass includes skeletal muscle, although the two terms should not be treated as synonymous. Skeletal muscle is particularly important because it contributes to physical strength, mobility and glucose disposal and becomes increasingly valuable as we age.
The question surrounding GLP-1-based treatments is therefore not whether lean mass decreases at all, but whether the amount lost is proportionate and whether appropriate nutrition and exercise can help preserve functionally important skeletal muscle.
The current evidence needs to be interpreted carefully. Some discussions have implied that GLP-1 medications uniquely “melt muscle”, which goes beyond what the evidence supports. A 2026 systematic review of randomised trials concluded that lean mass reductions were generally proportional to overall weight loss when these medications were used alongside lifestyle interventions. However, other reviews have found that lean tissue can represent a substantial proportion of total weight lost and have emphasised the limited evidence regarding optimal strategies for protecting muscle during treatment. PubMed
Current American Diabetes Association guidance estimates that lean-body-mass reductions commonly account for approximately 25–30% of total weight reduction with GLP-1-based obesity medications, while also emphasising that physical function and quality of life generally improve with weight loss. This is an important piece of nuance. Loss of lean mass deserves attention, particularly in older adults and those already vulnerable to sarcopenia, but it should not automatically be interpreted as evidence that the treatment is damaging muscle health. Diabetes Journals
The sensible response is to make muscle preservation part of treatment from the beginning.
Protein becomes considerably more important when appetite disappears
Protein is therefore one of the first things I would consider when looking at somebody's diet during GLP-1 treatment.
When total food intake decreases substantially, protein intake can easily decrease with it. Somebody who previously consumed three substantial meals might now tolerate two very small ones. Unless those meals are deliberately constructed, achieving an appropriate protein intake can become difficult.
Current ADA obesity-treatment guidance recommends paying particular attention to protein intake in people using obesity medications. It suggests at least 60 grams of protein per day as a general minimum, while noting that higher intakes, commonly around 1.2–1.6 g/kg/day, are often recommended during weight reduction. These figures need individual interpretation, particularly in people with conditions such as chronic kidney disease, and there remains a need for better GLP-1-specific trials establishing optimal protein requirements. Diabetes Journals
This is where food choice becomes important. If appetite is extremely limited, filling the available dietary space with foods that contribute little protein or micronutrient value is a missed opportunity.
Eggs, fish, poultry, lean meat, Greek-style yoghurt, cottage cheese, tofu, tempeh, beans and lentils can all contribute depending on somebody's dietary preferences and tolerance. Where whole-food intake is insufficient, an appropriate protein-rich drink or other convenient source may occasionally be useful, although there is no reason to assume everybody using these medications requires protein supplements.
The objective is not to turn every meal into a bodybuilding exercise. It is simply to recognise that when food volume falls, nutrient density has to rise.
Resistance training belongs alongside the medication
Protein alone is only part of the muscle-preservation story.
Muscle needs a reason to remain.
Resistance exercise provides that stimulus. During weight reduction, combining adequate protein with regular muscular loading gives the body a stronger signal to preserve skeletal muscle than simply increasing protein while remaining sedentary.
This is now reflected in clinical guidance. The ADA specifically recommends adequate protein intake alongside muscle-strengthening activity to minimise muscle loss during obesity treatment and cites evidence that resistance training during calorie restriction can substantially improve lean-mass preservation. Diabetes Journals
This is particularly important for people entering middle and older age. Someone can achieve an impressive reduction on the bathroom scales while simultaneously losing tissue they will spend the next decade wishing they had preserved.
Weight is therefore only one outcome worth measuring. Waist circumference, strength, fitness, metabolic markers and, where appropriate, body composition provide a much richer picture of what is happening.
Micronutrients are the quieter concern
Protein and muscle have attracted much of the attention around GLP-1 nutrition, but micronutrients may prove equally important.
These medications do not produce the same malabsorptive state associated with certain forms of bariatric surgery. The nutritional concern arises primarily because people may simply consume considerably less food, potentially compounded by nausea, vomiting, altered food preferences or avoidance of particular food groups.
A recent review identified potential concerns around micronutrients including iron, vitamin B12, vitamin D, calcium and thiamine, while emphasising that formal GLP-1-specific nutritional guidance remains underdeveloped. Nature
The ADA's 2026 Standards similarly advise monitoring nutritional intake during obesity treatment and identify iron, calcium, magnesium, zinc and vitamins A, D, E, K, B1, B12 and C among nutrients that may warrant attention according to individual circumstances. The guidance suggests considering multivitamin and mineral supplementation in higher-risk situations, including very low energy intake, exclusion of nutrient-rich food groups, underlying malabsorption, older age or excessive weight loss. Diabetes Journals
This does not mean everybody taking semaglutide or tirzepatide should immediately buy an enormous collection of supplements. It means dietary adequacy should be assessed rather than assumed.
The distinction is important. Supplementation should correct or prevent a genuine nutritional problem, not become another commercial industry built around frightening people taking these medications.
Gastrointestinal symptoms can make good nutrition harder
Nausea, vomiting, diarrhoea, constipation and reflux are among the gastrointestinal effects commonly reported with GLP-1-based therapies. They are frequently more noticeable during dose escalation and may improve with time, but for some people they significantly influence what and how much they can eat. PubMed
Large, high-fat meals can be particularly difficult to tolerate when gastric emptying is slowed and appetite is reduced. Eating smaller portions, eating slowly and stopping when comfortably full may therefore become important practical strategies. Current ADA guidance also suggests reducing high-fat or spicy foods where these exacerbate gastrointestinal symptoms. Diabetes Journals
The important point is that persistent gastrointestinal symptoms should not simply be celebrated as evidence that the medication is “working”. If somebody is routinely vomiting, unable to maintain adequate hydration or struggling to consume nutritionally adequate food, that requires discussion with the prescribing healthcare professional. Dose escalation is not a competition, and current guidance explicitly supports individualising dose and titration according to response and tolerability. Diabetes Journals
Fibre and fluid still matter
Constipation is another common practical problem, and reduced food intake can mean reduced fibre intake almost by default. Somebody who previously consumed several meals containing vegetables, fruit, pulses or whole grains may now eat much smaller quantities of all of them.
Fibre intake therefore deserves deliberate attention, although increasing it aggressively in somebody already experiencing significant gastrointestinal symptoms may make matters worse. The appropriate amount and source need to be tailored to tolerance.
Fluid intake can also fall. Interestingly, the September 2026 review of nutrient intake notes evidence that these medications may reduce overall water intake as well as food intake. PubMed
This makes hydration something worth consciously monitoring rather than assuming thirst will always take care of it. Requirements vary substantially according to body size, climate, activity, diet and medical conditions, and people with heart failure, kidney disease or other conditions affecting fluid management need individual advice rather than generic hydration targets.
Food quality matters more, not less
One of the strangest ideas surrounding GLP-1 medications is that nutrition somehow becomes less important because the drug controls appetite.
I would argue almost the opposite.
If somebody previously consumed 2,500 calories and now comfortably consumes 1,500, there is simply less dietary space available in which to obtain protein, essential fats, fibre, vitamins, minerals and phytochemicals. Each meal therefore has more nutritional work to do.
This is where the concept of nutrient density becomes genuinely useful.
Vegetables, fruit, high-quality protein foods, nuts, seeds, pulses, whole grains where appropriate, oily fish and unsaturated fats can deliver substantial nutritional value without requiring enormous portions. The exact combination will depend on preferences, tolerance, metabolic health and medical circumstances, but the principle remains the same.
Conversely, if appetite is tiny and much of the available intake is occupied by confectionery, alcohol, snack foods or other foods with relatively low micronutrient density, it becomes increasingly difficult for the remainder of the diet to compensate.
The medication can control appetite. It cannot choose the food.
Rapid weight loss is not automatically better weight loss
The dramatic effectiveness of modern obesity medication has inevitably created competition around numbers. Twenty kilograms lost. Twenty-five per cent of body weight gone. Another clothing size down.
These can represent enormously meaningful improvements in health, particularly for somebody living with severe obesity and related metabolic disease.
But the fastest possible rate of weight reduction should not automatically become the goal.
Very low energy intake increases the difficulty of achieving adequate protein and micronutrient intake and may increase the amount of lean tissue lost. Rapid weight reduction can also increase gallstone risk, an issue recognised in the wider literature on substantial weight loss.
The ADA recommends screening for micronutrient deficiencies in people experiencing particularly rapid or substantial weight loss and emphasises monitoring nutritional intake throughout obesity treatment. Diabetes Journals
The aim should therefore be successful treatment, not nutritional attrition.
What happens if the medication eventually stops?
Nutrition has another role that extends beyond the period of active weight loss.
GLP-1-based obesity medications are increasingly regarded as long-term treatments because discontinuation commonly results in substantial weight regain. Current ADA guidance notes that trials stopping semaglutide or tirzepatide have observed recurrence of a substantial proportion of lost weight within the following year, alongside deterioration in some of the cardiometabolic improvements achieved during treatment. Diabetes Journals
This makes the idea that somebody can simply use medication to lose weight and worry about diet afterwards particularly problematic.
The period of appetite suppression is an opportunity to establish a dietary pattern that can support long-term health: learning how to build satisfying meals, consuming adequate protein, increasing dietary quality, resistance training, becoming more physically active and identifying an eating structure that remains realistic.
None of this guarantees that weight will remain stable if medication is discontinued. The biological drivers of appetite may return strongly, and some people will appropriately remain on treatment long term. But medication and nutrition should not be viewed as competing approaches.
They are doing different jobs.
The nutrition conversation around GLP-1s needs to catch up
Semaglutide, tirzepatide and related medications represent a genuine advance in obesity treatment. Their effectiveness should not be minimised simply because they are pharmacological treatments, and concerns about nutrition should not be weaponised to suggest that people would somehow be better off remaining with untreated obesity.
At the same time, successful obesity treatment should involve more than producing the lowest possible number on a set of scales.
A person can lose a substantial amount of weight and improve their metabolic health while also paying careful attention to protein, micronutrients, muscle, fibre, hydration and overall dietary quality. Indeed, the more powerful our weight-loss treatments become, the more important these considerations are likely to become.
The emerging research reflects this. Recent reviews repeatedly identify the same gap: the drugs have advanced faster than the nutritional infrastructure surrounding them. We have remarkably effective medications capable of dramatically reducing food intake, but comparatively little high-quality research establishing the optimal dietary strategy during treatment. PubMed
For now, the sensible approach is not complicated. Nutritional intake should be assessed rather than assumed. Protein should be prioritised and combined with resistance exercise where appropriate. Meals should be nutrient dense. Fibre and hydration should receive attention. Persistent gastrointestinal symptoms should be managed rather than endured, and people with very low intake, rapid weight loss or other risk factors may require closer nutritional monitoring.
The purpose of GLP-1 treatment is not to make somebody extraordinarily good at not eating. It is to help treat obesity and improve health. Nutrition remains fundamental to that objective, even when appetite is being powerfully controlled by medication.
References:
Sorić T, Sarić A, Ivanišin A, et al. Hidden Malnutrition in the GLP-1 Era: Micronutrient Status, Protein Adequacy, and Lean Mass as Emerging Nutritional Considerations—A Narrative Review. Nutrients. 2026;18(17):2757. doi:10.3390/nu18172757. This is particularly useful for the sections on reduced food intake, protein adequacy, micronutrients, muscle health and identifying people at greater nutritional risk. PubMed
American Diabetes Association Professional Practice Committee for Obesity. Pharmacologic Treatment of Obesity in Adults: Standards of Care in Overweight and Obesity. Diabetes, Obesity, and Cardiometabolic CARE. 2026;1(1):5–36. doi:10.2337/doci25-0008. This is a particularly strong reference because the 2026 guidance specifically recommends monitoring nutritional intake during obesity pharmacotherapy, ensuring adequate protein and combining this with muscle-strengthening activity. It also discusses micronutrient risk, gastrointestinal management and lean-mass preservation. DOI
American Diabetes Association Professional Practice Committee for Obesity, Gudzune KA. Pharmacologic Treatment of Obesity in Adults: Standards of Care in Overweight and Obesity. BMJ Open Diabetes Research & Care. 2026;13(Suppl 1):e005729. doi:10.1136/bmjdrc-2025-005729. This is the corresponding peer-reviewed publication of the obesity pharmacotherapy standards and provides additional authoritative support for positioning medication alongside nutrition and lifestyle intervention rather than treating the drug as a substitute for them. PubMed
Urbina J, et al. Micronutrient and Nutritional Deficiencies Associated With GLP-1 Receptor Agonist Therapy: A Narrative Review. Clinical Obesity. 2026;16(1):e70070. doi:10.1111/cob.70070. This review is directly relevant to the article's discussion of vitamin D, iron, calcium, protein, thiamine and vitamin B12. Importantly, the authors acknowledge that much of the available evidence is observational, so causality between GLP-1 therapy and deficiencies has not yet been established. Wiley Online Library
Diet Quality and Micronutrient Intake among United States Adults Eligible for GLP-1 Receptor Agonist Antiobesity Medications: A Nationally Representative Analysis. The Journal of Nutrition. 2026;156(9):101753. doi:10.1016/j.tjnut.2026.101753. This newly published analysis is useful background because it examines diet quality and micronutrient adequacy in adults eligible for GLP-1 anti-obesity treatment, highlighting that nutritional vulnerability can exist before medication is even started.
